
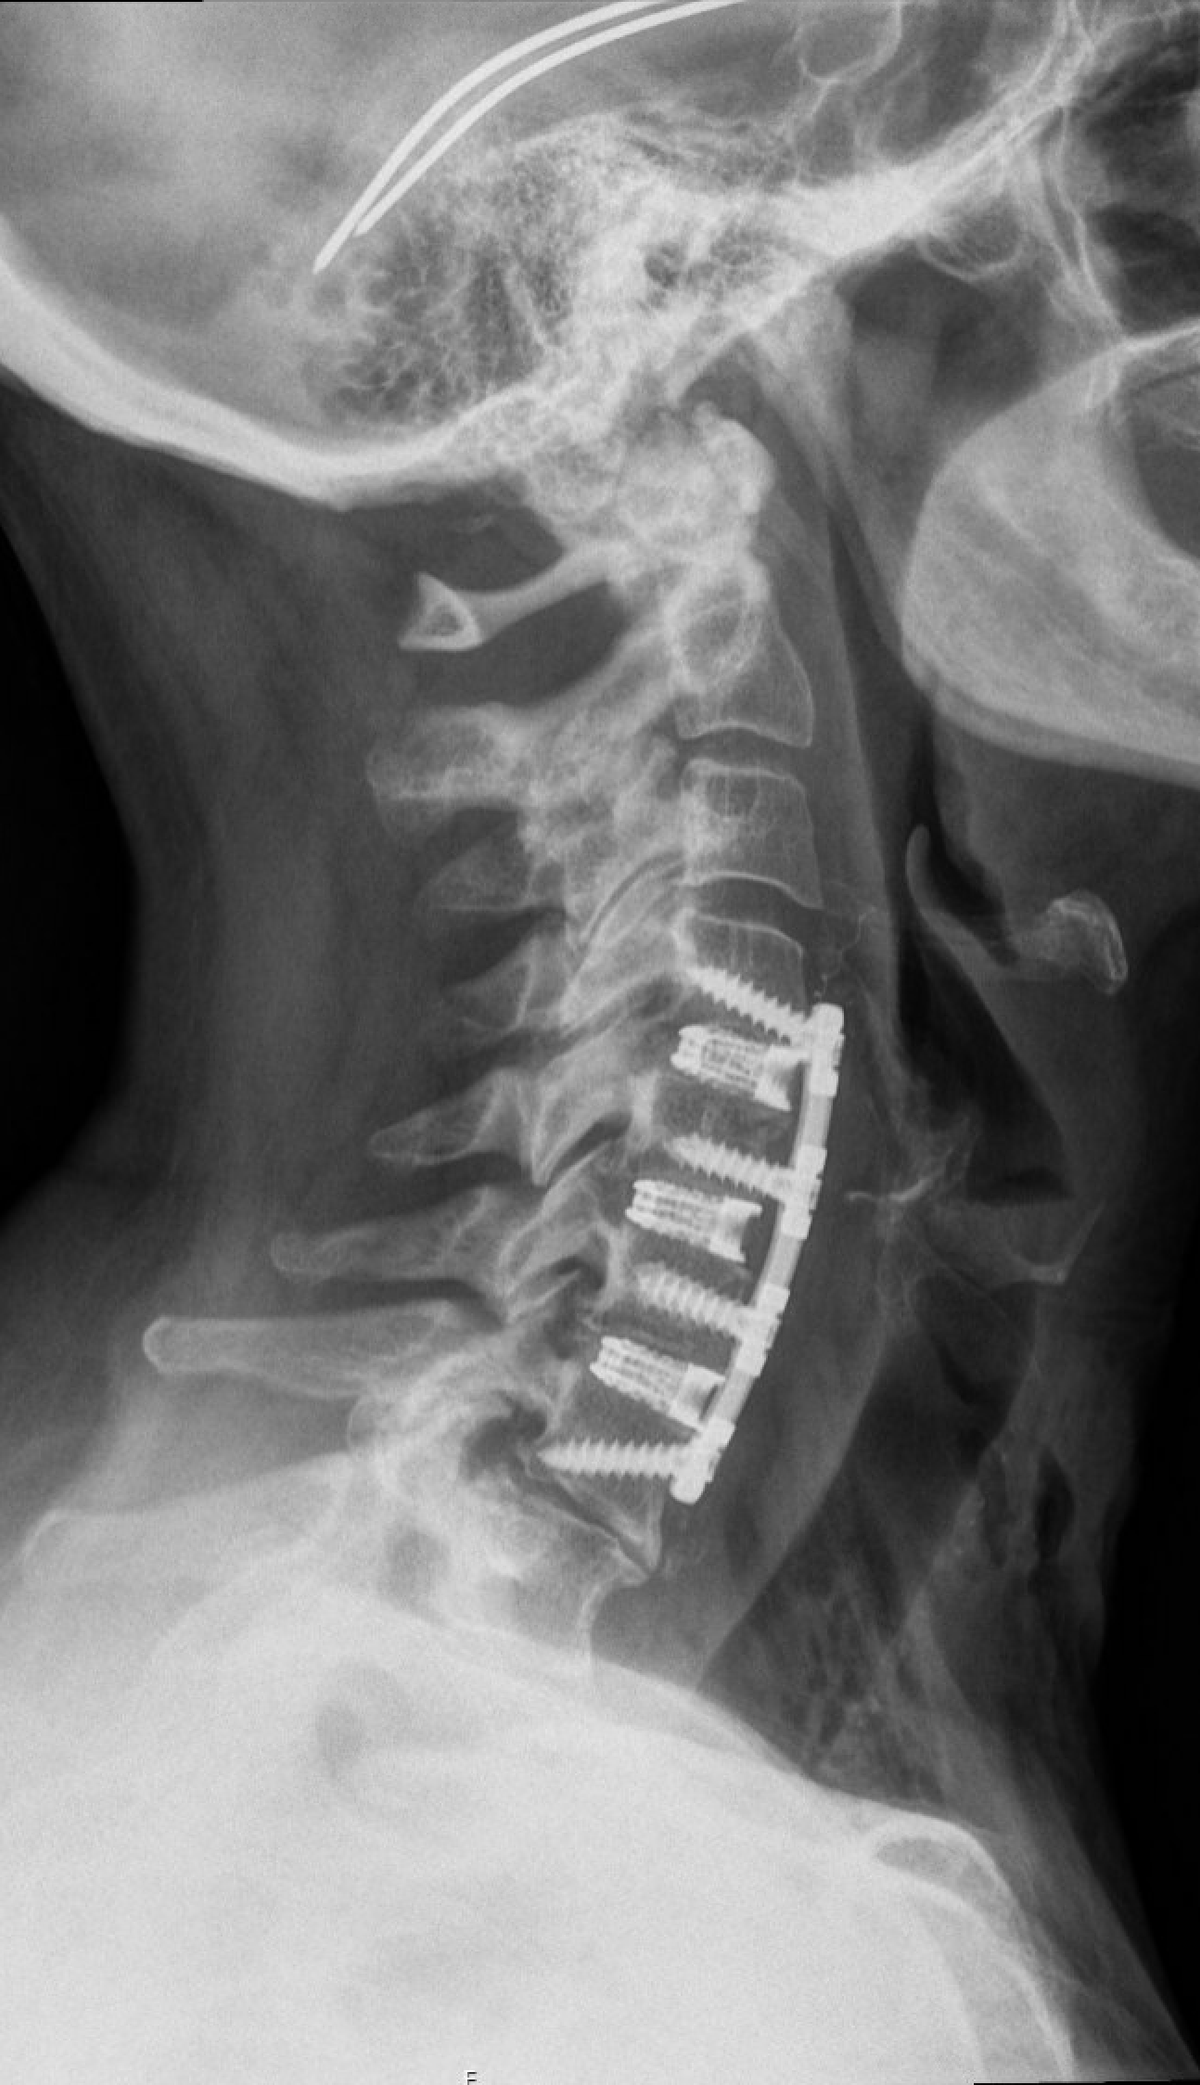
Anterior Cervical Discectomy & Fusion (ACDF) Surgery in Los Angeles
Orthopedic Spine Surgeon — Long Beach & Torrance, CA
Medically reviewed by Brandon A. Ortega, MD · Last updated September 14, 2026
Anterior cervical discectomy and fusion (ACDF) is a proven surgical treatment for cervical disc herniation, spinal stenosis, radiculopathy, and spinal cord compression. The procedure removes the damaged disc, decompresses the spinal cord and nerves, restores disc height, and stabilizes the affected level through fusion. Dr. Brandon Ortega performs ACDF in Los Angeles for patients whose cervical anatomy, instability, degeneration, or spinal alignment makes fusion the most appropriate treatment.
Overview
85-95%
patient satisfaction at 10-year follow-up
< 1
night hospital stay
6-12 Wks
average return to full activity
What Is Anterior Cervical Discectomy & Fusion?
Anterior cervical discectomy and fusion, commonly called ACDF, is a procedure used to relieve pressure on the spinal cord or nerves in the neck while stabilizing the affected portion of the cervical spine. The procedure is performed through a small incision in the front of the neck. The damaged disc is removed, along with any disc fragments, bone spurs, or other tissue compressing the spinal cord or nerve roots. The disc space is then restored with an implant or spacer containing bone-graft material. As healing occurs, the adjacent vertebrae gradually fuse together into one stable segment.
ACDF accomplishes two important goals simultaneously:
- Decompression: relieving pressure on the spinal cord and nerves.
- Stabilization: creating a solid fusion across an unstable or degenerative spinal segment.
Who is a Candidate?
ACDF may be appropriate for patients with cervical radiculopathy, myelopathy, spinal stenosis, disc herniation, instability, or advanced degenerative changes when symptoms have not improved with appropriate nonsurgical treatment. Surgery may be recommended sooner when there is progressive weakness, loss of coordination, difficulty walking, or significant spinal cord compression.
Levels Treated
ACDF can be performed at a single cervical level or across multiple levels depending on the location and extent of disease. The most treated levels are between C3 and C7.
The Implant
After the damaged disc is removed, an interbody spacer or cage is placed between the vertebrae to restore disc height and support fusion. Depending on the patient's anatomy and the number of levels being treated, additional fixation such as a cervical plate and screws may be used to provide stability while fusion develops.
A Proven Procedure
ACDF has been performed for decades and remains one of the most established operations in cervical spine surgery. Its ability to simultaneously decompress the neural structures and stabilize the cervical spine makes it applicable to a broad range of cervical conditions.
Benefits
Why Choose ACDF?
For appropriately selected patients, ACDF provides reliable decompression while creating long-term stability at the diseased spinal level.
Direct Nerve Decompression
Removing the damaged disc and bone spurs creates additional space around compressed nerve roots and the spinal cord. This can improve arm pain, numbness, tingling, weakness, and other neurological symptoms caused by cervical compression.
Restores Disc Height
The interbody implant restores the height of a collapsed disc space, helping reopen the neural foramina where the cervical nerves exit the spine.
Stabilizes the Spine
Fusion eliminates abnormal or painful movement at an unstable spinal segment and creates a stable foundation for long-term healing.
Corrects Alignment
ACDF can help restore cervical disc height and alignment in patients with degenerative collapse, segmental deformity, or instability.
Treats Advanced Degeneration
Unlike cervical disc replacement, ACDF does not require preservation of normal motion at the treated segment. This makes fusion an important option for patients with advanced spondylosis, instability, poor facet-joint function, or anatomy that is not appropriate for disc replacement.
Single and Multilevel Treatment
ACDF can treat disease involving one or multiple cervical levels when clinically appropriate.
ACDF vs. CDR
Anterior Cervical Discectomy & Fusion vs. Cervical Disc Replacement
Both ACDF and cervical disc replacement begin with the same fundamental goal: remove the damaged disc and completely decompress the spinal cord and nerves. The major difference is what happens to the spinal segment afterward.
Anterior Cervical Discectomy & Fusion
✓ Removes the damaged disc and decompresses the nerves ✓ Provides immediate structural stability ✓ Appropriate for a broad range of cervical pathology ✓ Can address instability and certain deformities ✓ Well established for single and multilevel disease ✓ Decades of clinical experience – Eliminates motion at the fused level – Requires biological bone healing – Fusion may take several months to mature – Carries a risk of pseudarthrosis or nonunion – May increase stress on adjacent spinal levels over time
Cervical Disc Replacement
✓ Removes the damaged disc and decompresses the nerves ✓ Preserves motion at the treated level ✓ Avoids the need for fusion ✓ No pseudarthrosis risk ✓ May reduce stress on adjacent spinal segments ✓ Often allows a faster return to unrestricted activity – Requires appropriate facet joints and bone quality – Not appropriate for significant instability – May not be appropriate with advanced spondylosis – Patient anatomy and implant indications may limit eligibility
Which Procedure Is Right for Me?
There is no single operation that is best for every cervical spine problem. Dr. Ortega performs both ACDF and CDR, allowing the surgical recommendation to be based on the patient's anatomy rather than forcing every patient into one treatment philosophy.
For younger or active patients with preserved motion, healthy facet joints, and suitable anatomy, cervical disc replacement may allow motion to be preserved.
When significant instability, advanced degeneration, deformity, poor facet-joint function, or other contraindications to disc replacement are present, ACDF may provide the more reliable long-term reconstruction.
The goal is not simply to avoid fusion. The goal is to choose the operation most likely to provide durable neurological decompression, spinal stability, and long-term function.
Recovery
What to Expect After ACDF
Recovery begins immediately after surgery, although the biological fusion process continues for several months. Arm pain caused by nerve compression may improve quickly after decompression. Numbness, weakness, balance problems, or symptoms caused by longstanding spinal cord compression may improve more gradually.
Day of Surgery
Same-Day or Overnight Stay
ACDF is performed under general anesthesia through a small incision in the front of the neck. Patients begin walking shortly after surgery. Depending on the number of levels treated, overall health, swallowing, pain control, and neurological function, patients may return home the same day or remain overnight for observation. Temporary throat soreness, difficulty swallowing, or hoarseness can occur following the anterior approach.
1–2 Weeks
Early Recovery at Home
Walking is encouraged from the beginning of recovery. Patients gradually increase normal daily activities while avoiding heavy lifting, strenuous activity, and excessive neck movement. A cervical collar may be prescribed depending on the procedure and surgeon's recommendations. Many patients notice early improvement in arm pain as pressure on the affected nerve is relieved.
3–6 Weeks
Return to Light Activity
Many patients can gradually return to driving, desk work, and light occupational activity during this period depending on their neurological recovery, pain level, medications, and type of work. Follow-up X-rays are used to evaluate spinal alignment, hardware position, and early healing. Physical therapy may begin as healing progresses.
6–12 Weeks
Progressive Return to Activity
Strengthening, cardiovascular exercise, and more demanding activities are gradually introduced. Many patients experience substantial functional recovery during this period, although heavy lifting, high-impact exercise, and certain recreational activities may remain restricted until adequate healing is confirmed.
Long Term
Solid Fusion and Durable Stability
The biological fusion continues after the patient feels functionally recovered. New bone gradually forms across the treated segment, creating a stable bridge between the vertebrae. Fusion maturation may continue for six months or longer, and follow-up imaging helps determine when more demanding activities can safely resume.
Ready to Find Out if ACDF Is Right for You?
Anterior Cervical Discectomy & Fusion (ACDF) Surgery in Los Angeles Q&A
What Is ACDF Surgery?
Anterior cervical discectomy and fusion, or ACDF, is a cervical spine procedure that removes a damaged or herniated disc through an incision in the front of the neck. The spinal cord and nerves are decompressed, and a spacer containing bone-graft material is placed between the adjacent vertebrae so they can gradually fuse together.
What Conditions Does ACDF Treat?
ACDF may be used to treat:
- Cervical disc herniation
- Cervical radiculopathy
- Cervical spinal stenosis
- Cervical degenerative disc disease
- Cervical spondylosis
- Bone spurs
- Cervical myelopathy
- Spinal cord compression
- Disc-space collapse
- Cervical instability
- Selected cervical deformities
- Certain traumatic injuries
The diagnosis on an MRI alone does not determine whether surgery is necessary. Imaging findings should correlate with the patient's symptoms and neurological examination.
What Symptoms Can ACDF Improve?
ACDF is particularly effective when symptoms are caused by identifiable compression of a cervical nerve or the spinal cord. Symptoms may include:
- Pain traveling from the neck into the shoulder or arm
- Numbness or tingling
- Hand or arm weakness
- Loss of hand dexterity
- Difficulty with buttons or fine motor tasks
- Balance problems
- Difficulty walking
- Symptoms associated with cervical myelopathy
Patients with isolated neck pain without identifiable nerve or spinal-cord compression require particularly careful evaluation before surgery.
Who Is a Candidate for ACDF?
Candidates commonly have symptoms caused by cervical nerve or spinal-cord compression that have not adequately improved with appropriate nonsurgical care. ACDF may also be considered when there is progressive neurological weakness, significant spinal cord compression, cervical myelopathy, instability, or another condition where delaying surgery could allow neurological deterioration. The decision depends on symptoms, physical examination, imaging, spinal alignment, bone quality, number of affected levels, overall health, and treatment goals.
How Is ACDF Surgery Performed?
ACDF is performed through a small incision in the front of the neck. The surgeon reaches the cervical spine through natural tissue planes, removes the damaged disc, and decompresses the spinal cord and nerve roots. An interbody implant containing bone graft is then placed into the disc space to restore height and alignment. A plate and screws or another fixation system may also be used depending on the patient's anatomy and surgical plan.
How Many Levels Can Be Treated With ACDF?
ACDF may be performed at one or multiple cervical levels. The appropriate number of levels depends on where spinal cord or nerve compression exists, the patient's symptoms, spinal alignment, stability, and overall anatomy. Multilevel fusion may involve a longer healing period and can carry different risks than a single-level procedure.
What Is the Success Rate of ACDF?
ACDF has a long clinical track record and high success rates in appropriately selected patients. Published patient-education data report overall success rates in the range of approximately 85% to 95%, although outcomes vary depending on the diagnosis, number of levels treated, duration of neurological compression, patient health, and how success is defined. Surgery is generally more predictable for symptoms caused by identifiable nerve-root or spinal-cord compression than for nonspecific neck pain alone.
How Long Is Recovery After ACDF?
Patients usually begin walking shortly after surgery. Light daily activities gradually resume during the first several weeks, and many patients return to desk-based work within approximately three to six weeks depending on their individual recovery. More strenuous activity is gradually introduced over the following weeks and months. Functional recovery and biological fusion are different processes. A patient may feel significantly better before the vertebrae have completely fused. The fusion itself may continue maturing for six months or longer.
Will I Need a Neck Brace After ACDF?
Some patients are prescribed a cervical collar following ACDF. Whether a brace is needed and how long it should be worn depends on the number of levels treated, fixation method, bone quality, anatomy, and surgeon preference. Dr. Ortega provides individualized postoperative instructions based on the specific reconstruction performed.
When Can I Exercise After ACDF?
Walking begins early and is encouraged throughout recovery. More strenuous cardiovascular activity, resistance training, weightlifting, and high-impact exercise are gradually reintroduced based on clinical progress and follow-up imaging. Patients should not advance activity simply because pain has improved; the biological fusion requires additional time to mature.
How Is ACDF Different From Cervical Disc Replacement?
Both operations remove the damaged cervical disc and decompress the spinal cord or nerves. The difference is reconstruction. ACDF places an implant and bone graft between the vertebrae so the segment becomes permanently fused. Cervical disc replacement places a mobile artificial disc designed to maintain movement at the treated segment. Disc replacement may be preferred in appropriately selected patients when motion can safely be preserved. ACDF may be preferable when there is instability, advanced spondylosis, deformity, significant facet disease, or another condition that makes motion preservation inappropriate.
Is Cervical Disc Replacement Better Than ACDF?
Neither procedure is universally better. The appropriate procedure depends on the patient's anatomy and diagnosis. Cervical disc replacement offers important advantages for appropriately selected patients because it preserves motion and avoids fusion. ACDF remains an important reconstructive option when the affected spinal segment requires stabilization or when anatomy makes disc replacement inappropriate. Because Dr. Ortega performs both procedures, the recommendation can be tailored to the individual patient's cervical spine rather than to a single surgical technique.
What Are the Risks of ACDF?
As with any spinal operation, ACDF has potential risks. These may include infection, bleeding, hematoma, difficulty swallowing, voice changes, nerve injury, spinal-cord injury, persistent symptoms, implant-related complications, failure of fusion, adjacent-level degeneration, and the possibility of additional surgery. Individual risk depends on the patient's health, anatomy, number of levels treated, bone quality, nicotine use, and other factors.
What Is Pseudarthrosis?
Pseudarthrosis means that the vertebrae do not form a solid fusion after surgery. Risk can be influenced by several factors, including nicotine use, poor bone quality, nutritional status, medical conditions, the number of levels treated, and postoperative activity. Because ACDF depends on bone healing, optimizing these factors before and after surgery is an important part of treatment.
Does Smoking Affect Cervical Fusion?
Yes. Nicotine can interfere with the biological process required for bone healing and may increase the risk of nonunion. Patients undergoing cervical fusion may be asked to discontinue smoking, vaping, nicotine replacement products, and other sources of nicotine before surgery and throughout the fusion period.
Can I Live Normally After ACDF?
Yes. The goal of ACDF is to allow patients to return to an active and functional life after recovery. The fused spinal level will no longer move independently, but many patients do not notice a substantial difference in overall neck mobility, particularly after a single-level fusion. Activity recommendations vary depending on the extent of surgery and the patient's occupation, recreational activities, and long-term spinal health.
Does Insurance Cover ACDF?
ACDF is commonly covered by health insurance when medically necessary, although coverage depends on the individual insurance plan, diagnosis, documentation of previous treatment, and authorization requirements. The office can review insurance requirements and assist with the authorization process when surgery is recommended.
Where Can I Get ACDF Surgery in Los Angeles?
Patients considering ACDF should be evaluated by a spine surgeon experienced in both cervical fusion and motion-preserving cervical surgery. This allows the decision between ACDF, cervical disc replacement, hybrid reconstruction, or continued nonsurgical treatment to be based on the patient's individual anatomy and goals. Dr. Brandon Ortega evaluates patients in Long Beach and Torrance, California, serving patients throughout Los Angeles and Southern California.
Why Choose Ortega Spine?
Fellowship-Trained Expertise
Advanced subspecialty training in complex, minimally invasive, and motion-preserving spine surgery.
Motion-Preservation Techniques
Cervical and lumbar disc replacement designed to relieve pain while preserving motion at the treated level.
Conservative Care First
Care begins with the least invasive effective treatment, reserving surgery for when nonoperative options are no longer sufficient.
Two Convenient Locations
Personalized spine care in Long Beach and Torrance, conveniently serving patients throughout the greater Los Angeles area.

About Dr. Ortega
Brandon A. Ortega, MD, is a board-certified, fellowship-trained orthopedic spine surgeon who provides comprehensive and personalized spinal care to adults in Torrance and Long Beach, California. His dedication to helping each patient regain mobility, reduce pain, and improve their quality of life has earned the respect of everyone in the community struggling with neck and back pain.
Consultation
Get Expert Care with Anterior Cervical Discectomy & Fusion (ACDF) Surgery in Los Angeles
Request an appointment with Brandon A. Ortega, MD, and our team will contact you to schedule a personalized spine consultation.
Prefer to call? Contact us.